Infective endocarditis with heart block (root abscess)
Bedside summary
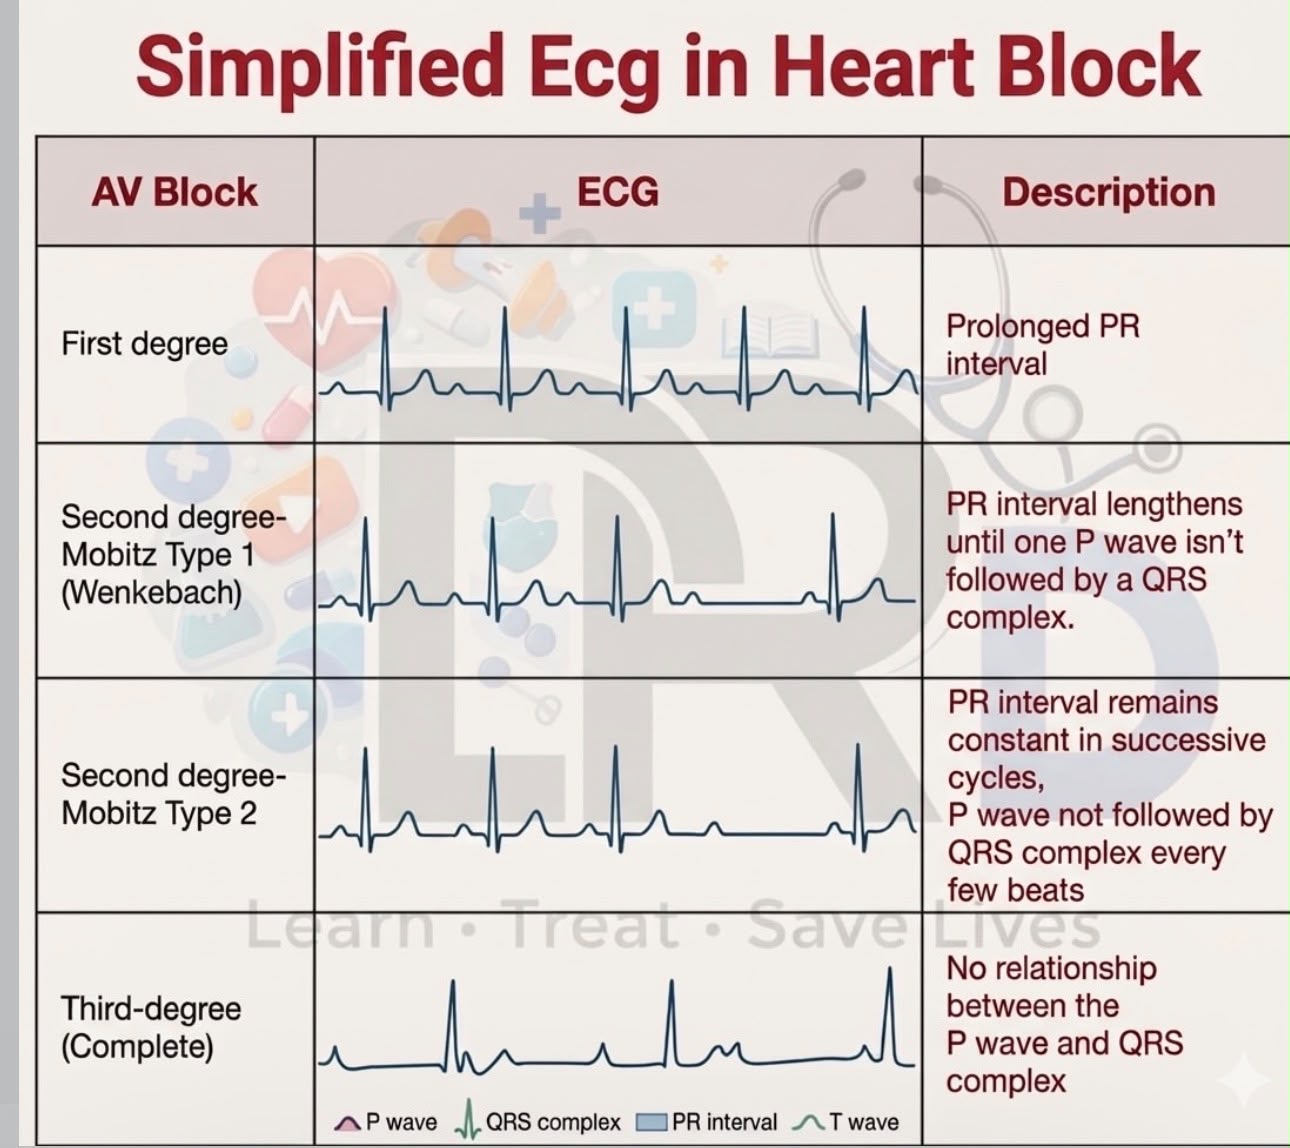
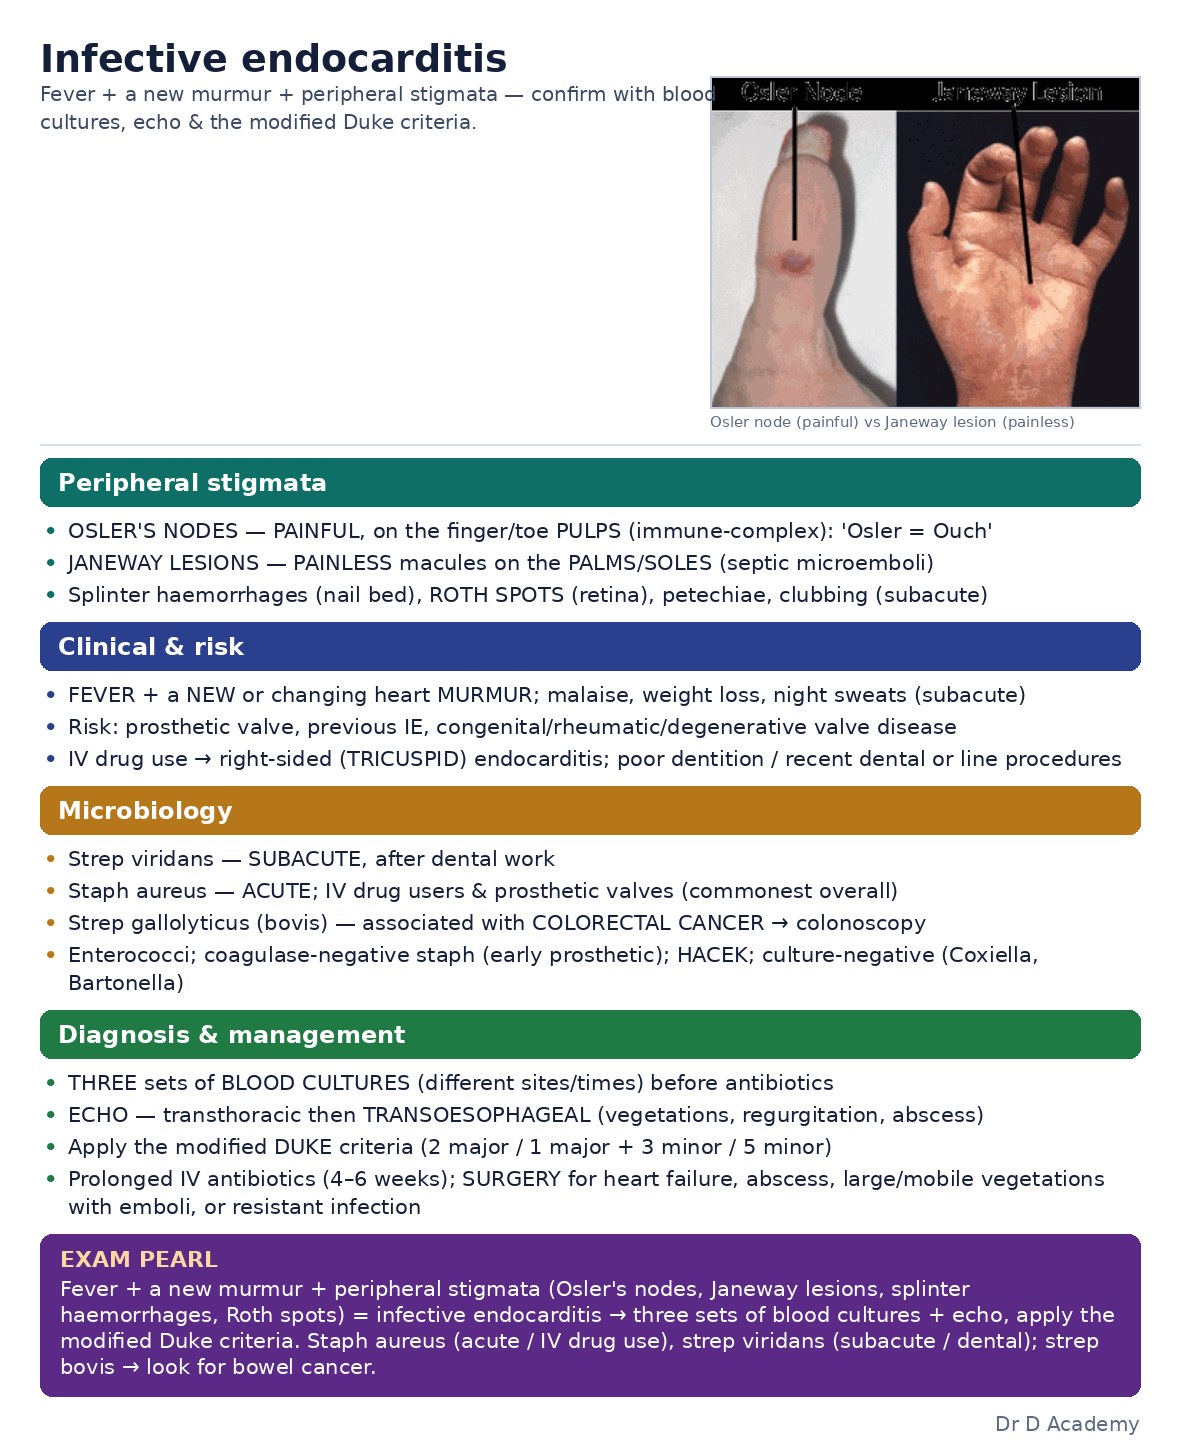
New conduction disease (PR prolongation or AV block) in infective endocarditis signals extension into the perivalvular tissue forming an aortic root abscess - a marker of severe disease needing urgent surgery. Antibiotics, monitoring and surgical referral are key.
Figures & algorithms
Assessment
Investigations
- Serial ECG (new PR prolongation/AV block) in endocarditis
- Transoesophageal echo (abscess, valve destruction)
- Blood cultures, inflammatory markers
Management
- Continue/optimise targeted IV antibiotics
- Continuous cardiac monitoring (may need temporary pacing for complete block)
- Urgent cardiology and cardiac-surgery referral (abscess usually needs surgery)
- Manage heart failure and embolic complications
- TOE to define the abscess
Drugs & doses
Disposition
A lengthening PR interval in endocarditis means an aortic root abscess is burrowing into the conduction system - get a TOE and call cardiac surgery. Antibiotic doses per BNF (current edition); confirm choice in the in-app Antibiotic Dosing tool.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.