Adrenal crisis in pregnancy
Adrenal · Endocrine
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
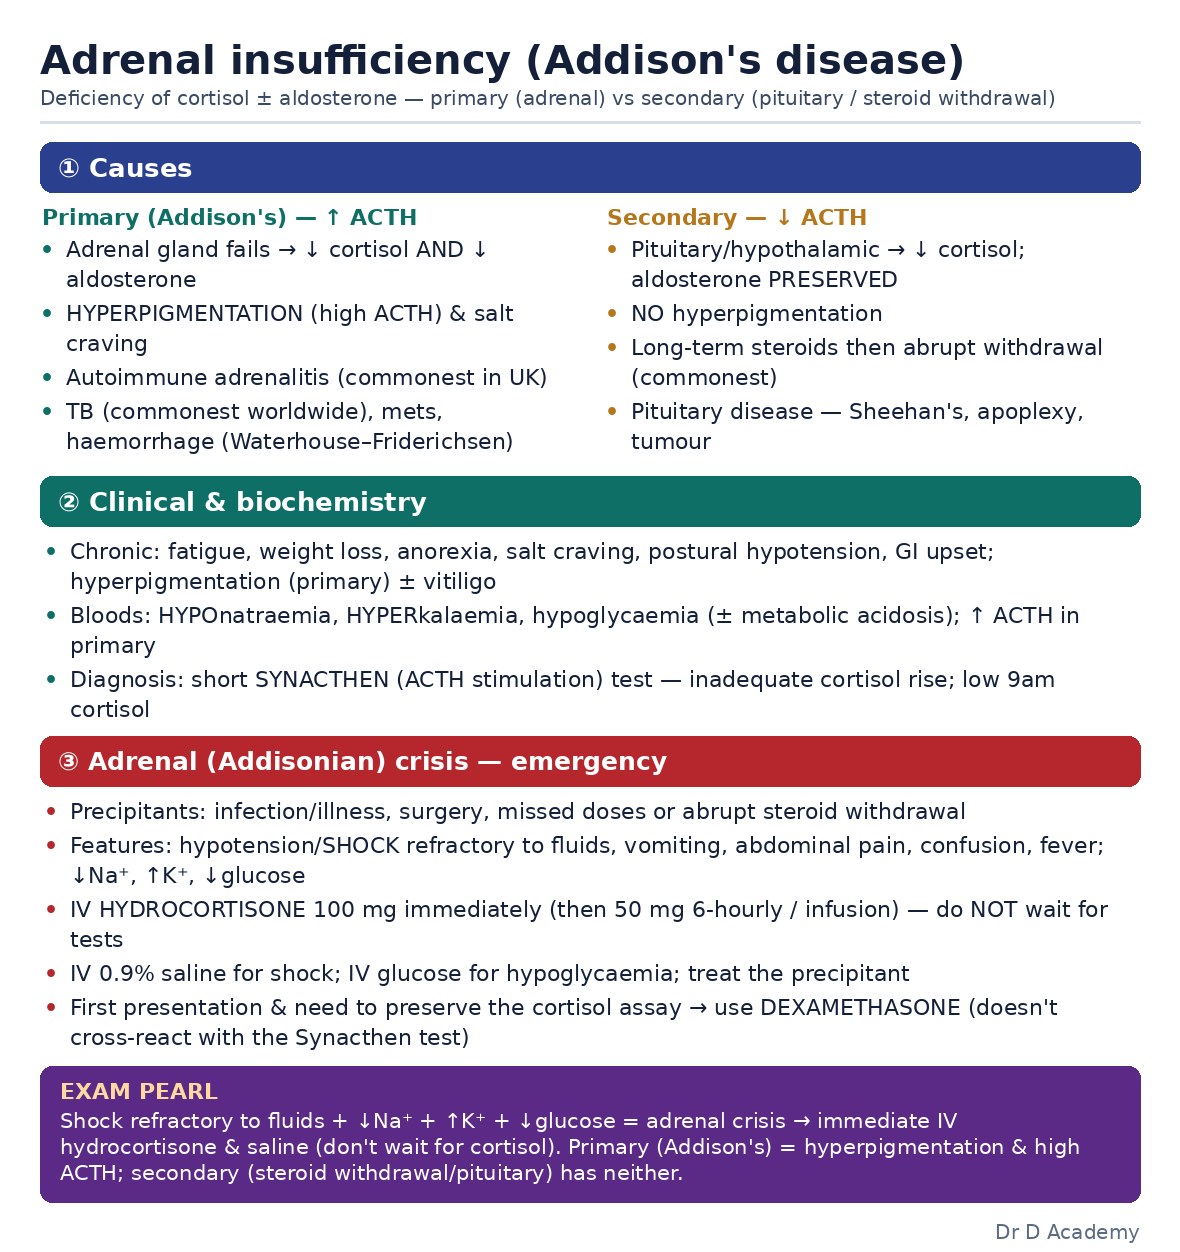
Acute adrenal insufficiency during pregnancy, labour or the postpartum period, precipitated by the stress of illness or delivery in a woman with known or unrecognised Addison disease. Presents with hypotension, vomiting, hyponatraemia and collapse.
Figures & algorithms
Red flags
- Hypotension unresponsive to fluids
- Reduced consciousness
- Severe hyponatraemia
- Fetal distress
Assessment
Differential diagnosis
- Hyperemesis gravidarum
- Sepsis
- Pre-eclampsia/HELLP
- Obstetric haemorrhage
- Sheehan syndrome (postpartum)
Investigations
- Electrolytes (hyponatraemia +/- hyperkalaemia), glucose
- Paired cortisol and ACTH (do not delay treatment)
- Septic screen for precipitant
- Assessment for obstetric causes of collapse
- Fetal monitoring as appropriate
Management
- Treat immediately on suspicion - give IV hydrocortisone without waiting for results
- Resuscitate with IV 0.9% sodium chloride and correct hypoglycaemia
- Give increased (stress) steroid cover around labour, delivery and illness
- Identify and treat the precipitant
- Monitor mother and fetus; involve endocrinology and obstetrics
- Plan peripartum steroid dosing and postpartum tapering
Drugs & doses
IV hydrocortisone (immediate and regular stress dosing, including in labour)
IV 0.9% sodium chloride resuscitation
IV glucose for hypoglycaemia
Fludrocortisone usually not needed while on high-dose hydrocortisone
Disposition
Admit; joint endocrine-obstetric care; peripartum steroid plan.
Complications & pitfalls
- Maternal and fetal death
- Circulatory collapse
- Missed diagnosis attributed to hyperemesis or sepsis
Exam pearls
- Increase steroid cover for the stress of labour and delivery in any woman with adrenal insufficiency
- Give hydrocortisone first; a low sodium with hypotension in pregnancy should raise the suspicion
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.