Eczema herpeticum
Infection · Dermatology
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
Disseminated herpes simplex infection of eczematous skin — monomorphic punched-out vesicles/erosions, systemic upset. Can be sight-threatening (periocular) and life-threatening.
Figures & algorithms
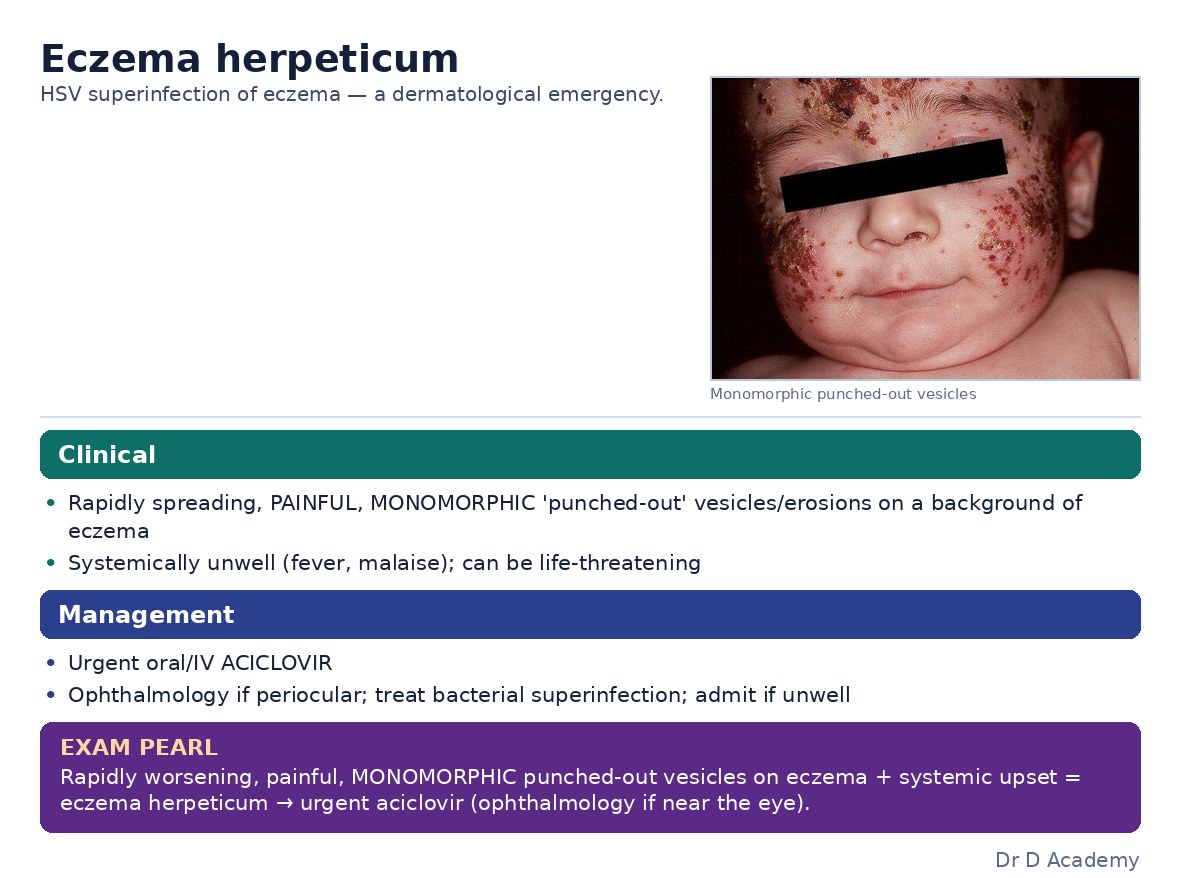
Red flags
- Periocular/eye involvement
- Systemic sepsis
- Rapid spread, immunosuppression
Assessment
Differential diagnosis
- Impetiginised eczema
- Chickenpox
- Disseminated zoster
- Hand-foot-mouth
Investigations
- Clinical diagnosis; viral swab (HSV PCR)
- Assess for ocular involvement; bloods if systemic
- Bacterial swab (secondary infection)
Management
- Start systemic aciclovir urgently (IV if severe/systemic/ocular)
- Ophthalmology referral if periocular/eye involvement
- Treat secondary bacterial infection; analgesia; fluids
- Dermatology referral; admit if extensive/systemic/immunosuppressed
- Avoid topical steroids on infected areas until controlled
Drugs & doses
Aciclovir (oral/IV)
Empirical antibiotics per BNF — see the in-app Antibiotic Dosing tool
Analgesia; fluids
Disposition
Admit if severe/ocular/systemic; dermatology + ophthalmology.
Complications & pitfalls
- Herpetic keratitis/blindness
- Sepsis, dissemination
- Death (rare)
Exam pearls
- Monomorphic punched-out lesions on eczema = eczema herpeticum
- Start aciclovir early; refer to ophthalmology if near the eye
- It is HSV, not just “infected eczema”
Start aciclovir promptly, cover secondary bacterial infection, and refer ophthalmology if periocular. Antibiotic doses per BNF (current edition); confirm choice in the in-app Antibiotic Dosing tool.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.