Ludwig’s angina
Deep space infection · Dental & Oral
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
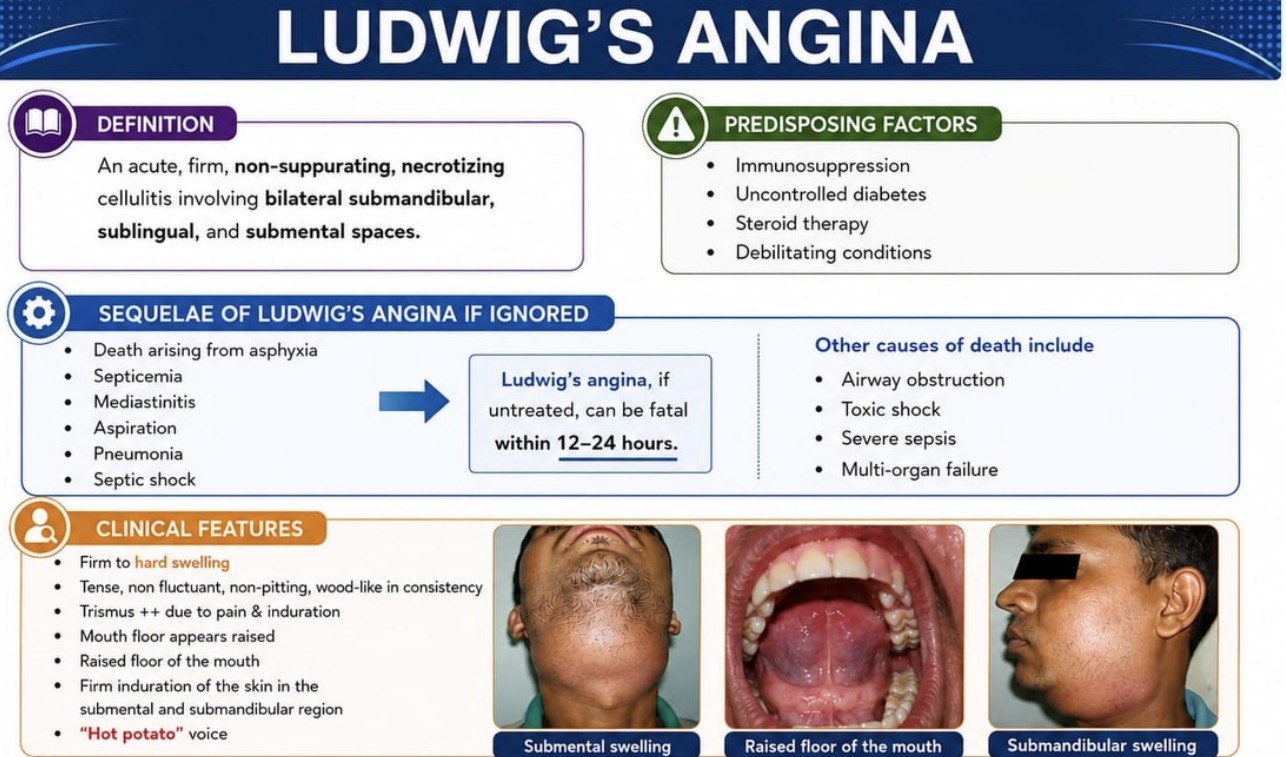
Rapidly spreading bilateral cellulitis of the submandibular, sublingual and submental spaces, usually from a lower molar infection. Floor-of-mouth swelling pushes the tongue up and back — a true airway emergency.
Figures & algorithms
Red flags
- Stridor, drooling, muffled “hot potato” voice
- Inability to lie flat / tripod posture
- Trismus, rapidly enlarging neck
- Hypoxia or rising work of breathing
Assessment
Differential diagnosis
- Peritonsillar/parapharyngeal abscess
- Epiglottitis
- Angioedema
- Salivary gland infection
- Deep neck space abscess
Investigations
- Clinical diagnosis — do not delay treatment for imaging
- CT neck with contrast if stable (extent/abscess)
- FBC, CRP, blood cultures, glucose
- Flexible nasendoscopy to assess airway
Management
- Prioritise the AIRWAY — senior anaesthetic + ENT/maxillofacial help early
- Sit upright; high-flow oxygen; prepare for difficult airway (awake fibreoptic / front-of-neck)
- IV broad-spectrum antibiotics covering anaerobes
- IV dexamethasone may reduce oedema
- Urgent surgical drainage of collections; do NOT lie the patient flat
Drugs & doses
IV co-amoxiclav or ceftriaxone + metronidazole
IV dexamethasone
Analgesia, IV fluids
Disposition
Theatre for drainage; ICU/HDU airway monitoring; ENT/maxillofacial admission.
Complications & pitfalls
- Complete airway obstruction
- Mediastinitis, necrotising fasciitis
- Sepsis
- Internal jugular thrombosis
Exam pearls
- The airway can occlude within minutes — definitive airway plan before sedation
- Never lie the patient flat
- Get ENT/maxfax and anaesthetics involved immediately
Airway first. Plan a definitive (often awake) airway with senior anaesthetics before anything else.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.