Necrotising fasciitis (soft tissue)
Surgical emergency · Dermatology
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
Rapidly progressive deep soft-tissue infection with fascial necrosis. Pain out of proportion, systemic toxicity, later skin changes/crepitus. Surgical emergency.
Figures & algorithms
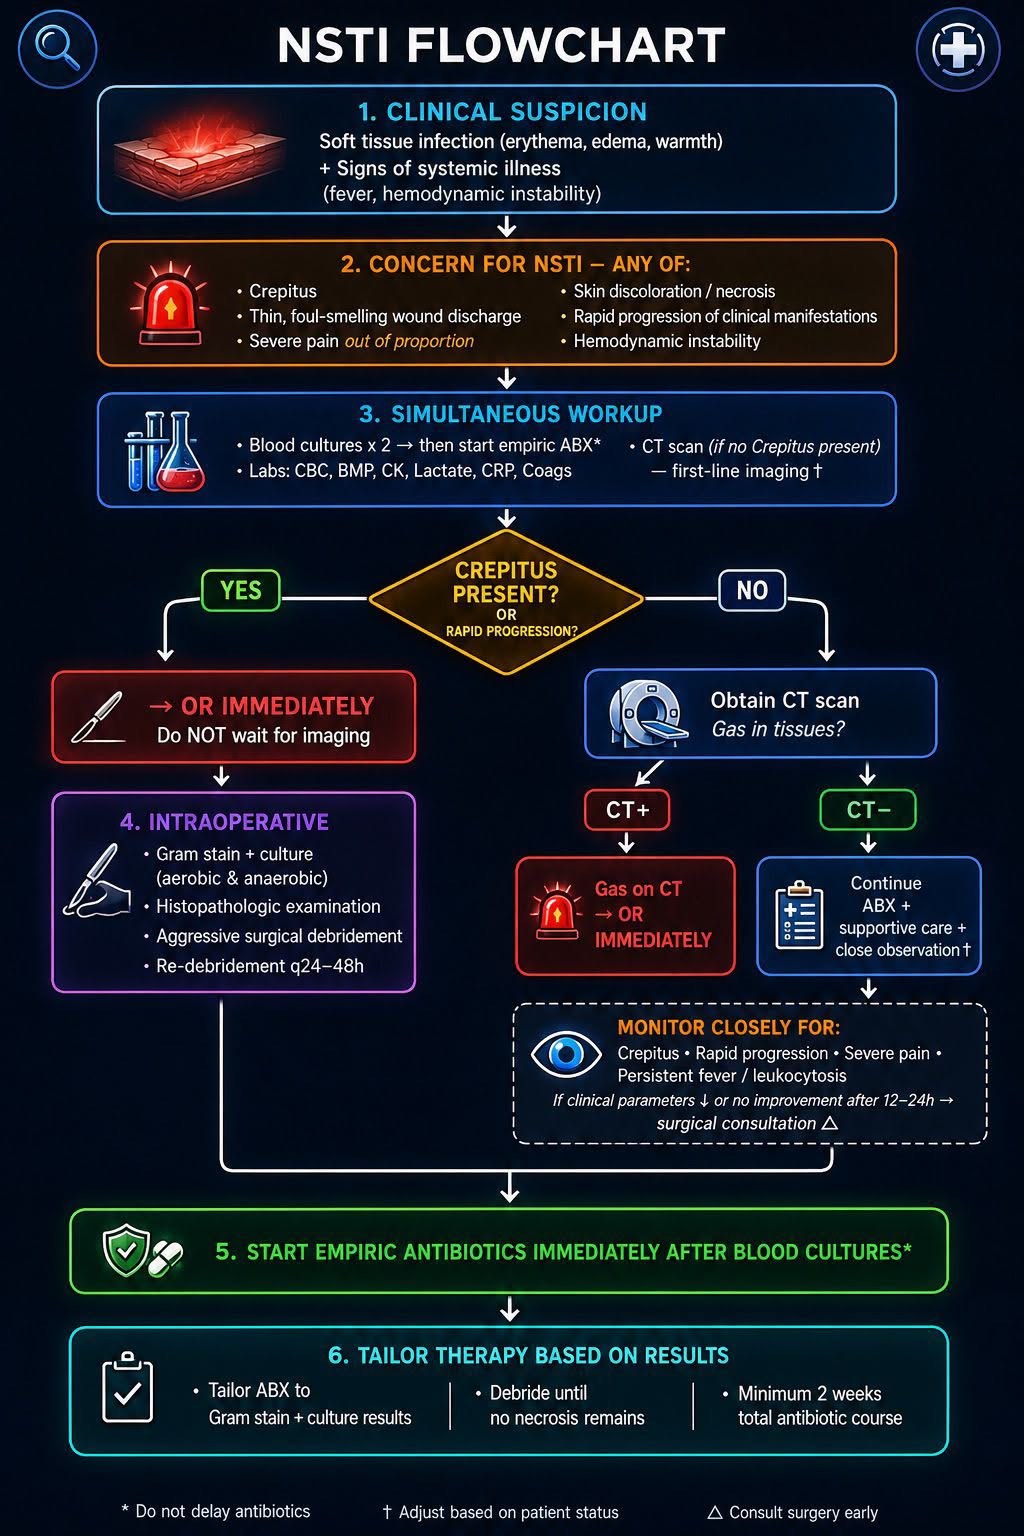
Red flags
- Pain out of proportion, rapid spread
- Crepitus, bullae, skin necrosis
- Septic shock
Assessment
Differential diagnosis
- Severe cellulitis
- Gas gangrene
- Abscess
- DVT
- Pyomyositis
Investigations
- Bloods incl. cultures, lactate, glucose, CK; LRINEC score
- Do not delay surgery for imaging
- Mark the spreading edge and time it
Management
- Aggressive resuscitation (sepsis six)
- Broad-spectrum antibiotics + clindamycin (toxin suppression)
- IMMEDIATE surgical debridement — definitive treatment
- Surgery + ICU; repeat debridements; do not delay for imaging
- Consider IVIG in streptococcal toxic shock (specialist)
Drugs & doses
Broad-spectrum antibiotics + clindamycin
IV fluids; vasopressors
IVIG (selected)
Disposition
Emergency theatre; ICU; surgery.
Complications & pitfalls
- Septic shock, multi-organ failure
- Limb/tissue loss
- High mortality
Exam pearls
- Pain out of proportion to skin findings is the early clue
- Surgery is the treatment; antibiotics are adjunctive
- Clindamycin suppresses toxin production
Resuscitate, give antibiotics + clindamycin, and get to theatre immediately — imaging must not delay surgery.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.