Chronic pancreatitis
GI / Hepatology · Gastroenterology
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
Progressive, irreversible pancreatic inflammation causing chronic pain and, eventually, exocrine (steatorrhoea) and endocrine (diabetes) failure. Management targets pain, pancreatic enzyme and nutritional replacement, diabetes, and removing the cause. First action: assess pain and nutrition, stop alcohol/smoking, and start pancreatic enzyme replacement if malabsorbing.
Figures & algorithms
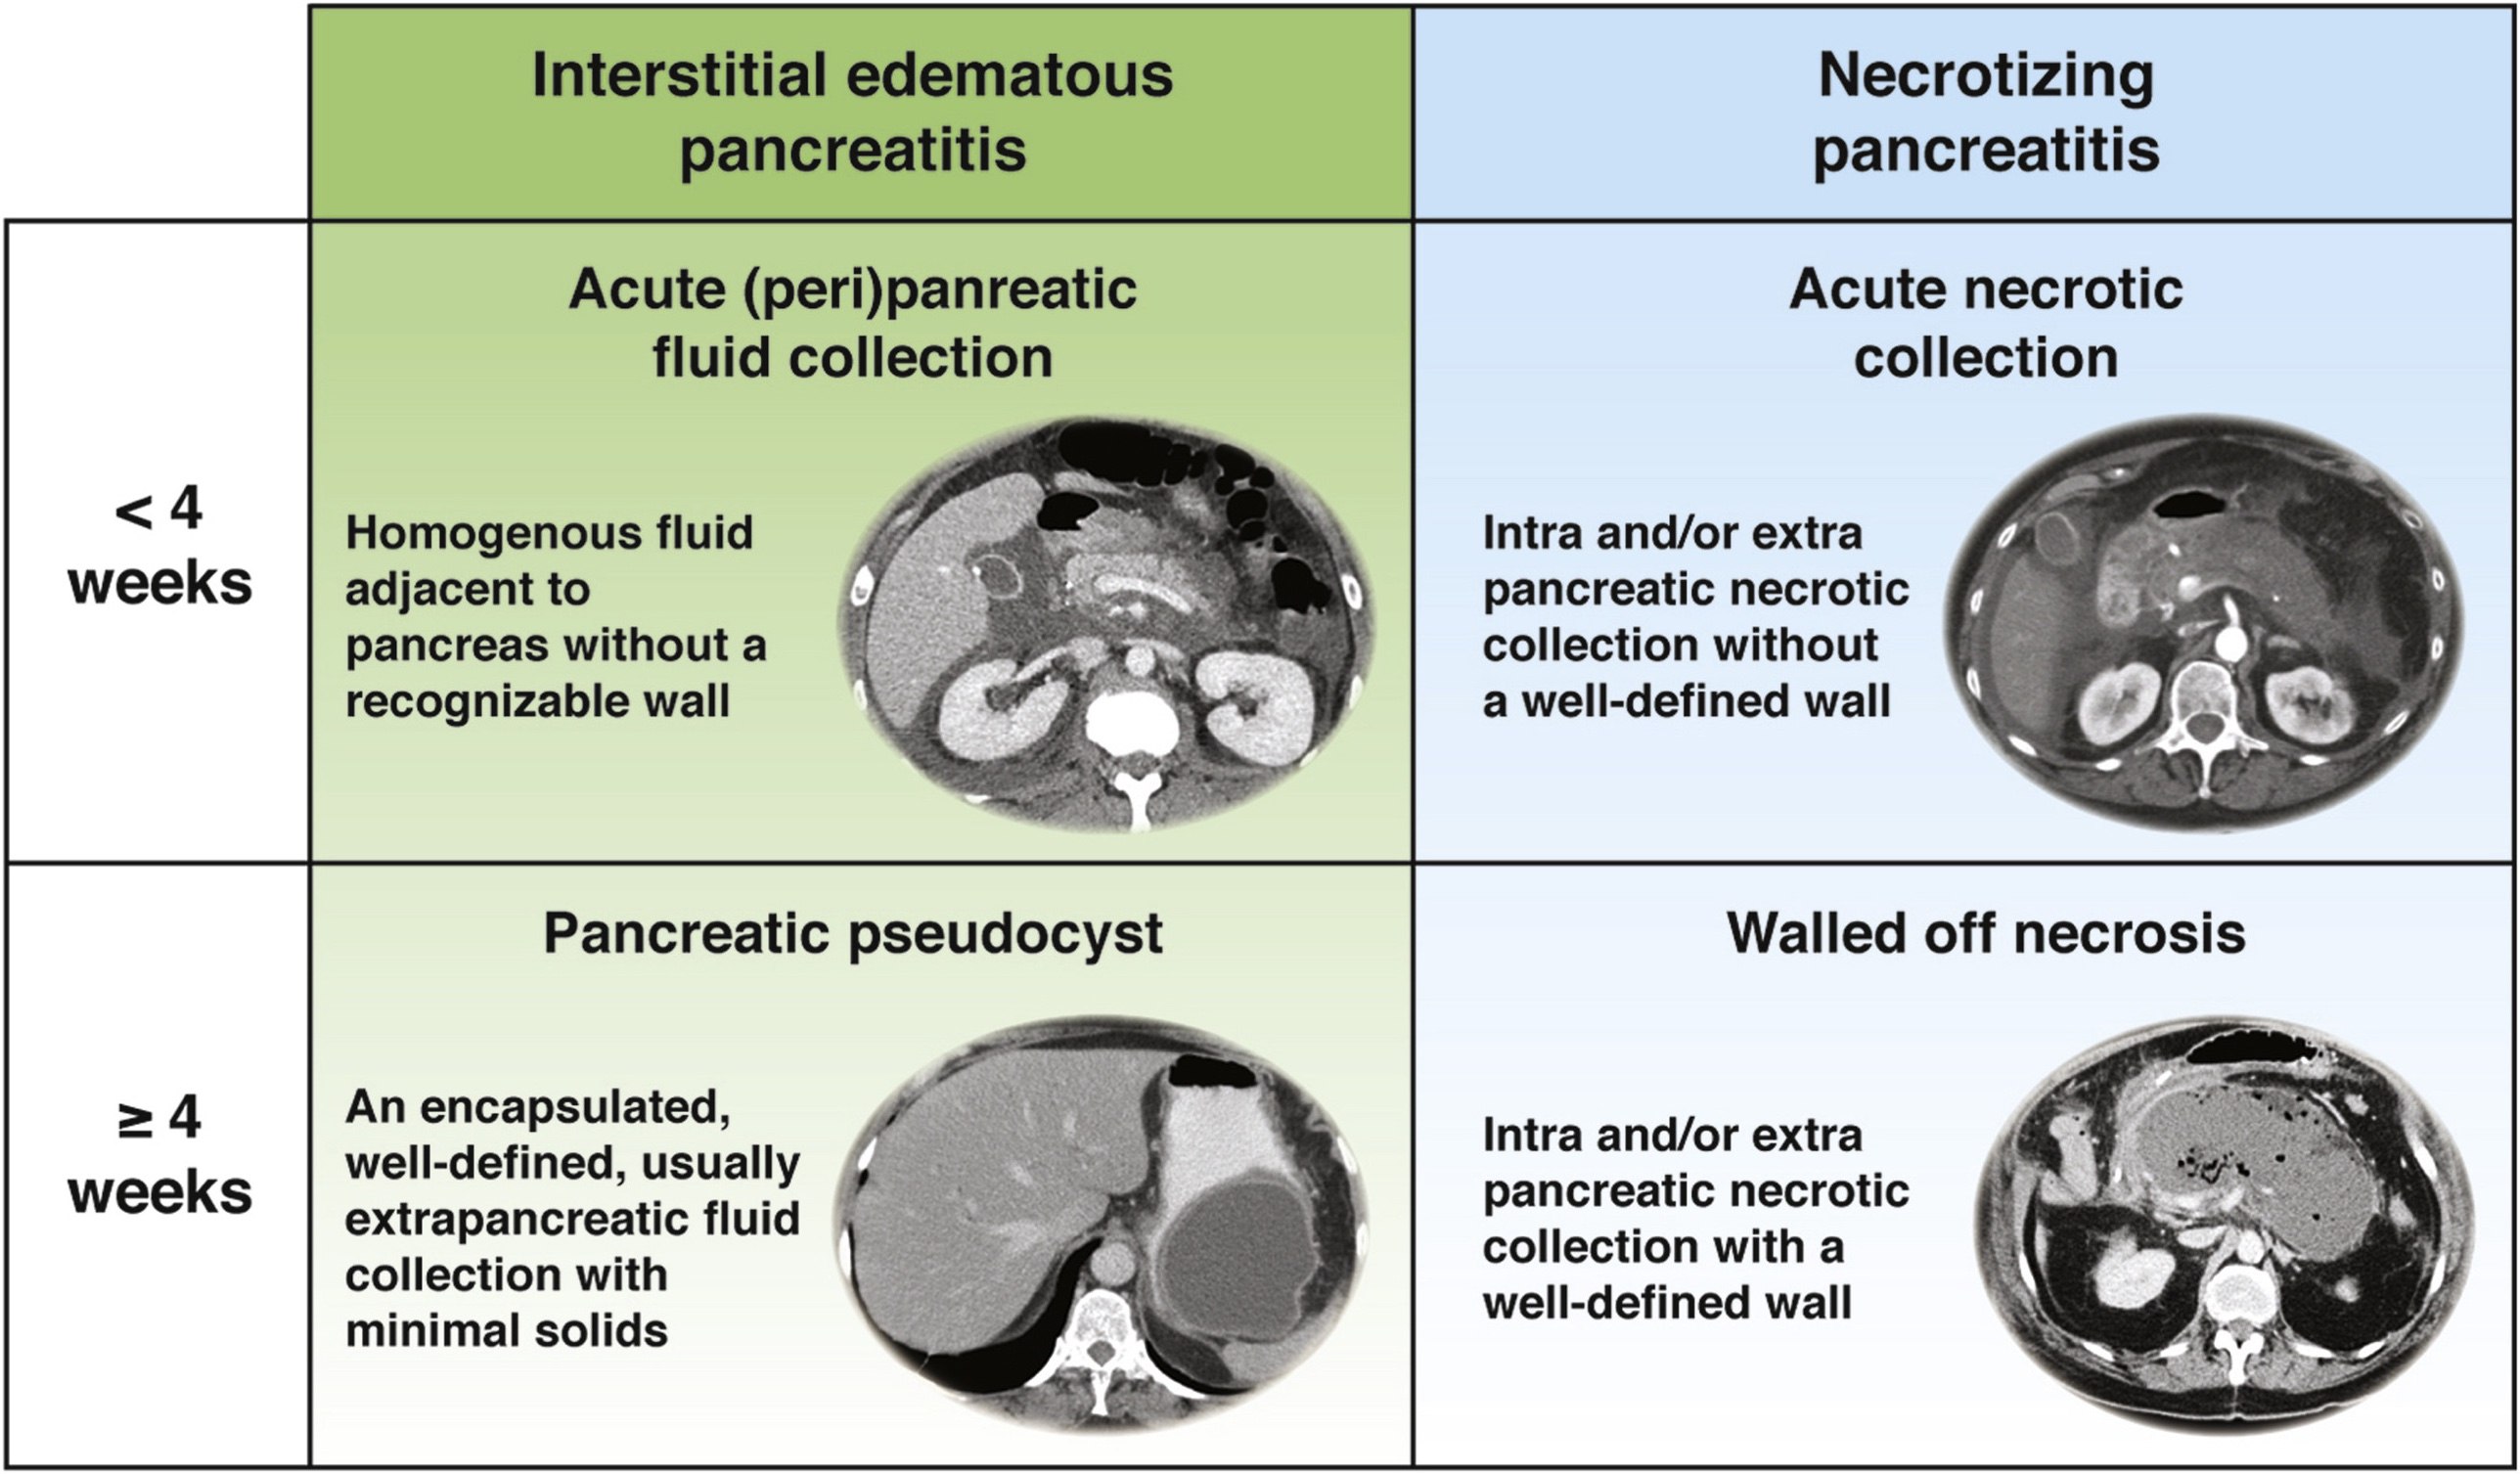
Red flags
- Refer to gastroenterology/pancreatic services for diagnosis, pain management and nutrition
- Admit for severe pain, acute-on-chronic attacks, or complications
- Urgent work-up for any suspicion of pancreatic cancer (new/worsening pain, weight loss, jaundice)
Assessment
Investigations
- CT or MRCP (calcification, ductal dilatation/strictures, atrophy); endoscopic ultrasound for early disease
- Faecal elastase (low in exocrine insufficiency);
- HbA1c/glucose
- Exclude pancreatic cancer and autoimmune pancreatitis (IgG4)
- Nutritional and fat-soluble vitamin assessment
Management
- Stop alcohol and smoking
- Pain: a stepwise analgesic approach, address modifiable causes, and consider coeliac-plexus block, endoscopic therapy (duct decompression/stones) or surgery for refractory pain
- Pancreatic enzyme replacement therapy with meals for steatorrhoea, plus a dietitian and fat-soluble vitamins
- Treat type 3c diabetes (often needs insulin)
- Surveillance for malignancy in high-risk/hereditary disease
Disposition
Refer to gastroenterology/pancreatic services for diagnosis, pain management and nutrition.
Complications & pitfalls
- Chronic pain and opioid dependence, malnutrition and osteoporosis, type 3c diabetes, pseudocysts, biliary or duodenal obstruction, splenic-vein thrombosis, and an increased risk of pancreatic cancer
Exam pearls
- New diabetes plus steatorrhoea and back pain in a drinker is pancreatic exocrine + endocrine failure (type 3c) — start pancreatic enzymes with meals and replace fat-soluble vitamins; and always keep pancreatic cancer on the radar.
- Monitoring & follow-up: Monitor weight/nutrition, HbA1c, fat-soluble vitamins and bone density; review enzyme replacement adequacy. Reinforce abstinence. Imaging surveillance where hereditary or concerning features exist.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.