Variceal haemorrhage
Bedside summary
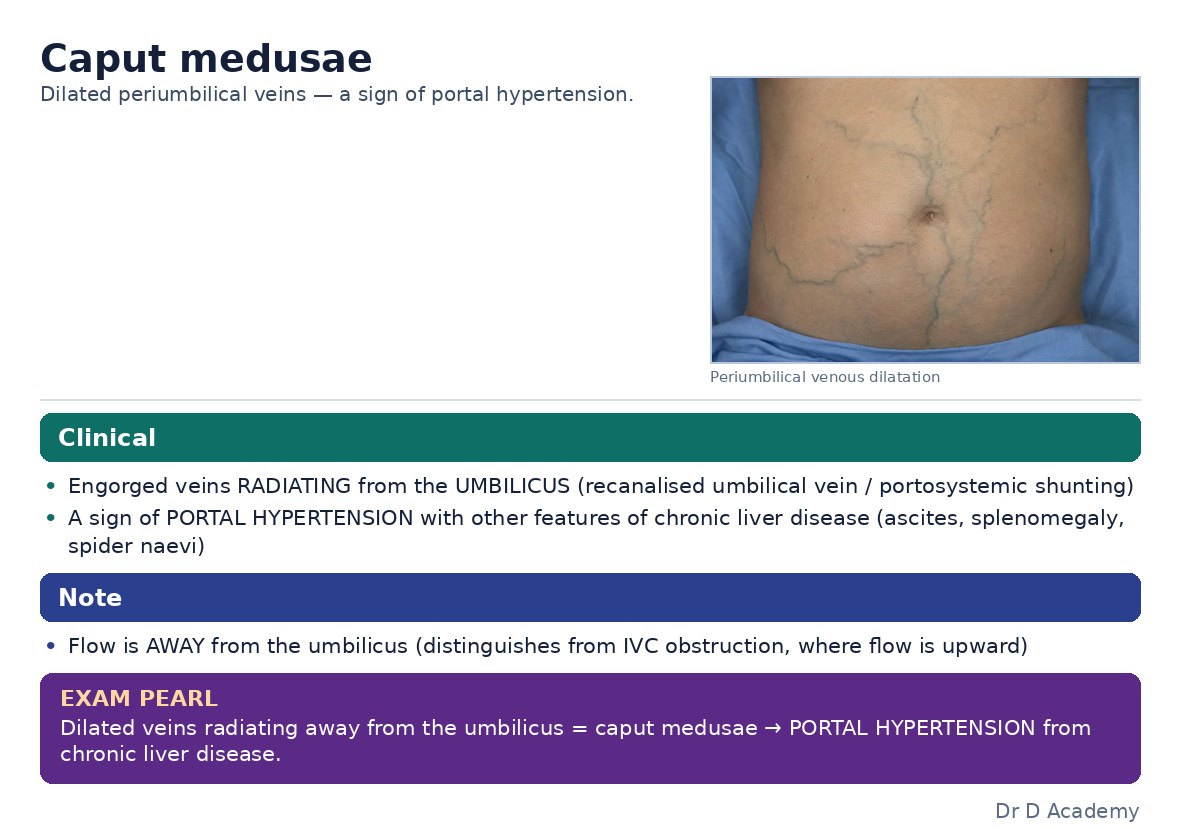
Bleeding from gastro-oesophageal varices — porto-systemic collaterals that form in portal hypertension (usually cirrhosis). It is a major cause of upper GI bleeding with high mortality, and management differs from non-variceal bleeding: alongside resuscitation and endoscopy it requires SPLANCHNIC VASOCONSTRICTORS and PROPHYLACTIC ANTIBIOTICS. Suspect a variceal source in any patient with chronic liver disease or known varices who presents with haematemesis or melaena.
Figures & algorithms
Red flags
- Haematemesis/melaena in known cirrhosis or portal hypertension
- Haemodynamic instability, massive bleeding, or airway compromise
- Failure to control bleeding at endoscopy (need tamponade/TIPS)
- Encephalopathy, sepsis or spontaneous bacterial peritonitis
- Coagulopathy of liver disease
Assessment
Differential diagnosis
- Non-variceal upper GI bleed (peptic ulcer, Mallory-Weiss, malignancy)
- Gastric variceal vs oesophageal variceal bleeding
- Portal hypertensive gastropathy
- Bleeding from a different source in a cirrhotic patient
Investigations
- FBC, U&E, LFTs, coagulation/fibrinogen, venous lactate, group & CROSSMATCH
- Assess severity/risk (e.g. Glasgow-Blatchford) and liver reserve (Child-Pugh/MELD)
- Urgent upper GI ENDOSCOPY (OGD) — diagnostic and therapeutic
- Cultures/ascitic tap if febrile or ascites (spontaneous bacterial peritonitis)
Management
- Resuscitate: A–E, two large-bore cannulae, activate MAJOR HAEMORRHAGE protocol if shocked; protect the AIRWAY early in massive haematemesis or encephalopathy (aspiration risk).
- RESTRICTIVE transfusion — target haemoglobin ~70–80 g/L (over-transfusion raises portal pressure and re-bleeding); correct significant coagulopathy/thrombocytopenia and fibrinogen judiciously; treat, don’t over-correct.
- Start a SPLANCHNIC VASOCONSTRICTOR early (before endoscopy): TERLIPRESSIN (or octreotide/somatostatin where terlipressin is unavailable/contraindicated).
- Give PROPHYLACTIC ANTIBIOTICS to every cirrhotic with GI bleeding (e.g. ceftriaxone) — they reduce infection, re-bleeding and mortality.
- Urgent ENDOSCOPY (within ~12 h once resuscitated): band LIGATION for oesophageal varices; cyanoacrylate GLUE injection for gastric varices.
- Uncontrolled bleeding → BALLOON TAMPONADE (Sengstaken-Blakemore/Minnesota tube) as a bridge, and early TIPS (transjugular intrahepatic porto-systemic shunt); consider pre-emptive TIPS in high-risk patients. Manage hepatic encephalopathy (lactulose) and continue vasoconstrictor + antibiotics.
Drugs & doses
Disposition
Complications & pitfalls
- Exsanguinating haemorrhage and death
- Aspiration pneumonia
- Hepatic encephalopathy; renal failure (hepatorenal)
- Infection / spontaneous bacterial peritonitis
- Oesophageal rupture/ulceration from tamponade or banding
Exam pearls
- Cirrhotic with a GI bleed needs THREE things beyond resuscitation: a vasoconstrictor (terlipressin), antibiotics (ceftriaxone), and urgent endoscopy.
- Transfuse restrictively (Hb 70–80 g/L) — over-transfusion increases portal pressure and re-bleeding.
- Protect the airway early — massive haematemesis + encephalopathy = high aspiration risk.
- Balloon tamponade is a temporary bridge to definitive therapy (repeat endoscopy or TIPS), not a treatment.
Treat variceal bleeding as a distinct emergency: resuscitate with a RESTRICTIVE transfusion target (Hb 70–80 g/L), start TERLIPRESSIN and PROPHYLACTIC CEFTRIAXONE early, protect the airway, and get urgent endoscopic band ligation (oesophageal) or glue (gastric); escalate uncontrolled bleeding to balloon tamponade and TIPS, and manage encephalopathy.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.