Bacterial meningitis
Bedside summary
A neurological and sepsis emergency. The classic triad (fever, neck stiffness, altered mental status) is present in only a MINORITY — but almost all patients have at least one of fever, neck stiffness or an altered conscious level; a petechial/purpuric non-blanching rash suggests meningococcaemia. Confirm with lumbar-puncture CSF: a NEUTROPHILIC pleocytosis, HIGH protein, LOW glucose (CSF:serum ratio), positive Gram stain/culture and bacterial PCR. Kernig’s and Brudzinski’s signs are insensitive.
Figures & algorithms
Exam pearls
- Treat first, investigate second — antibiotics + dexamethasone before the LP if there is any delay.
- The classic triad is often absent; suspect meningitis on fever + one of headache/neck stiffness/altered mentation.
- CT-before-LP only for specific red flags (focal signs, low/falling GCS, immunocompromise, seizures, papilloedema).
- Add Listeria cover (amoxicillin) in the > 50/immunocompromised, and aciclovir if encephalitic features.
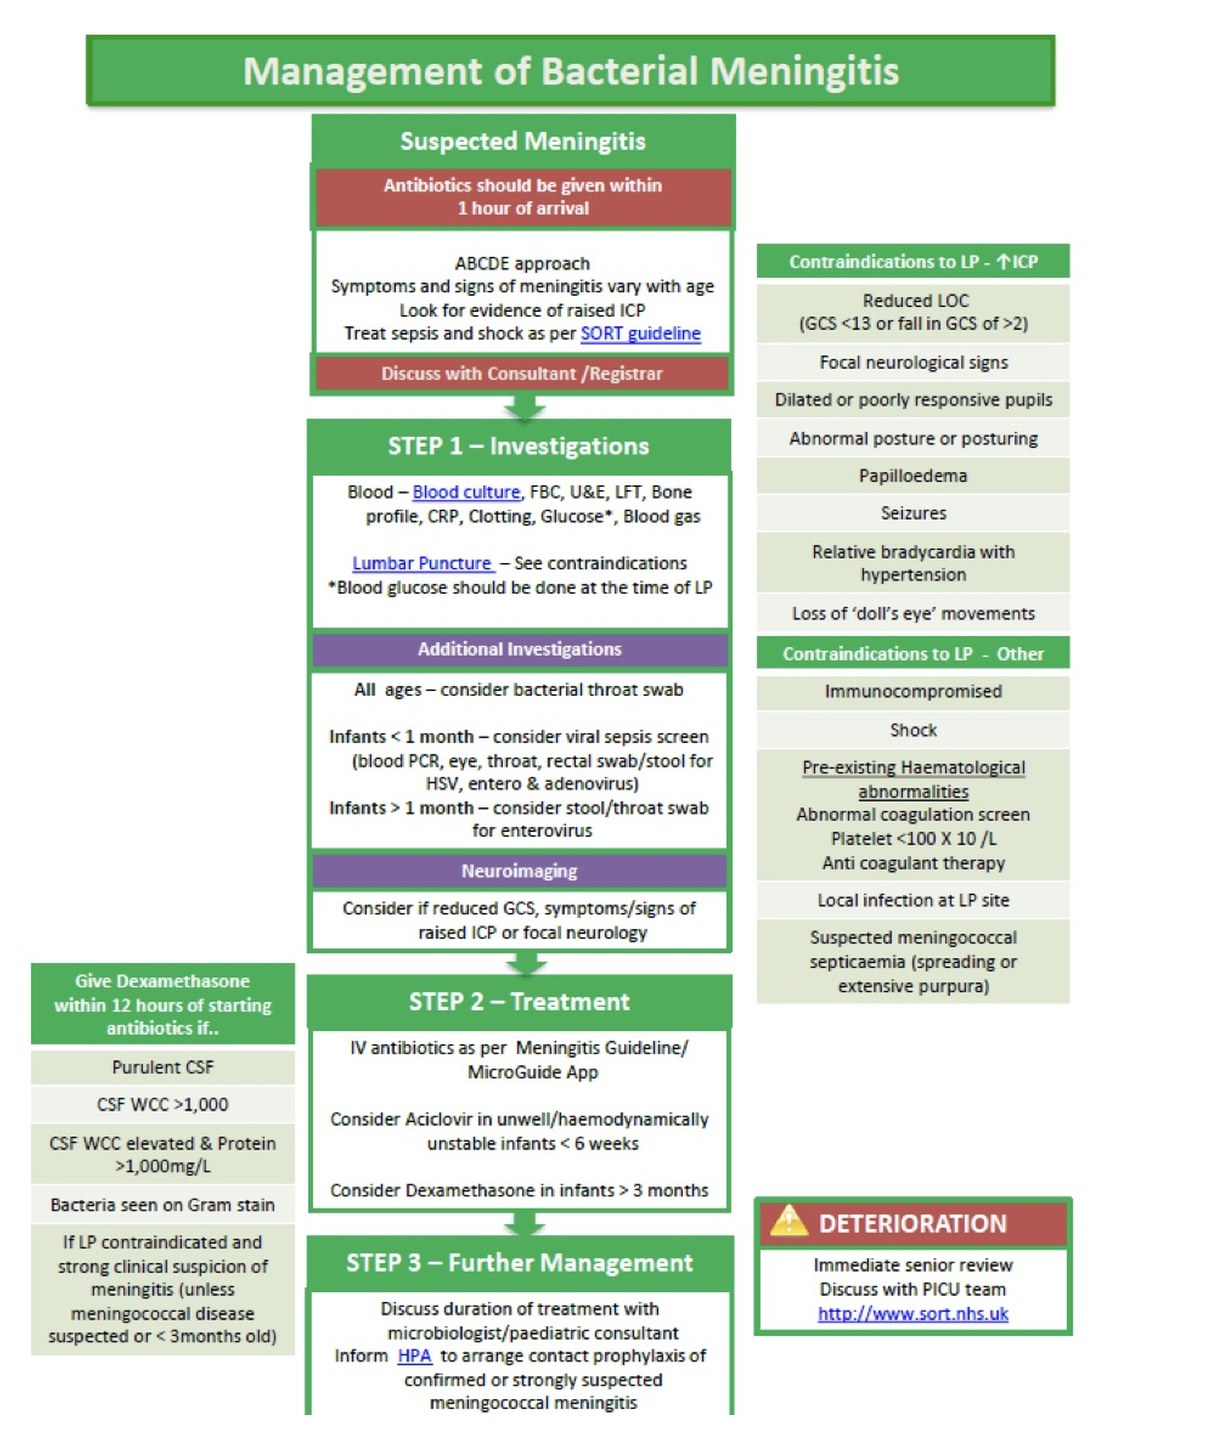
DO NOT DELAY antibiotics for imaging or LP — give empirical IV ceftriaxone the moment meningitis is suspected, with DEXAMETHASONE (with or just before the first antibiotic dose), ADD amoxicillin/ampicillin if age > 50 or immunocompromised (Listeria cover), and add aciclovir if encephalitis is possible. Take blood cultures first if it does not delay treatment. Do a CT before LP ONLY if there are focal neurological signs, reduced/deteriorating GCS, immunocompromise, new seizures or papilloedema — otherwise proceed to LP.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.