Herpes zoster (shingles) & post-herpetic neuralgia (incl. ophthalmic zoster, Ramsay Hunt, disseminated zoster)
Dermatomal vesicular rash + pain; antivirals <72h; eye & disseminated = urgent · Infectious Disease
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
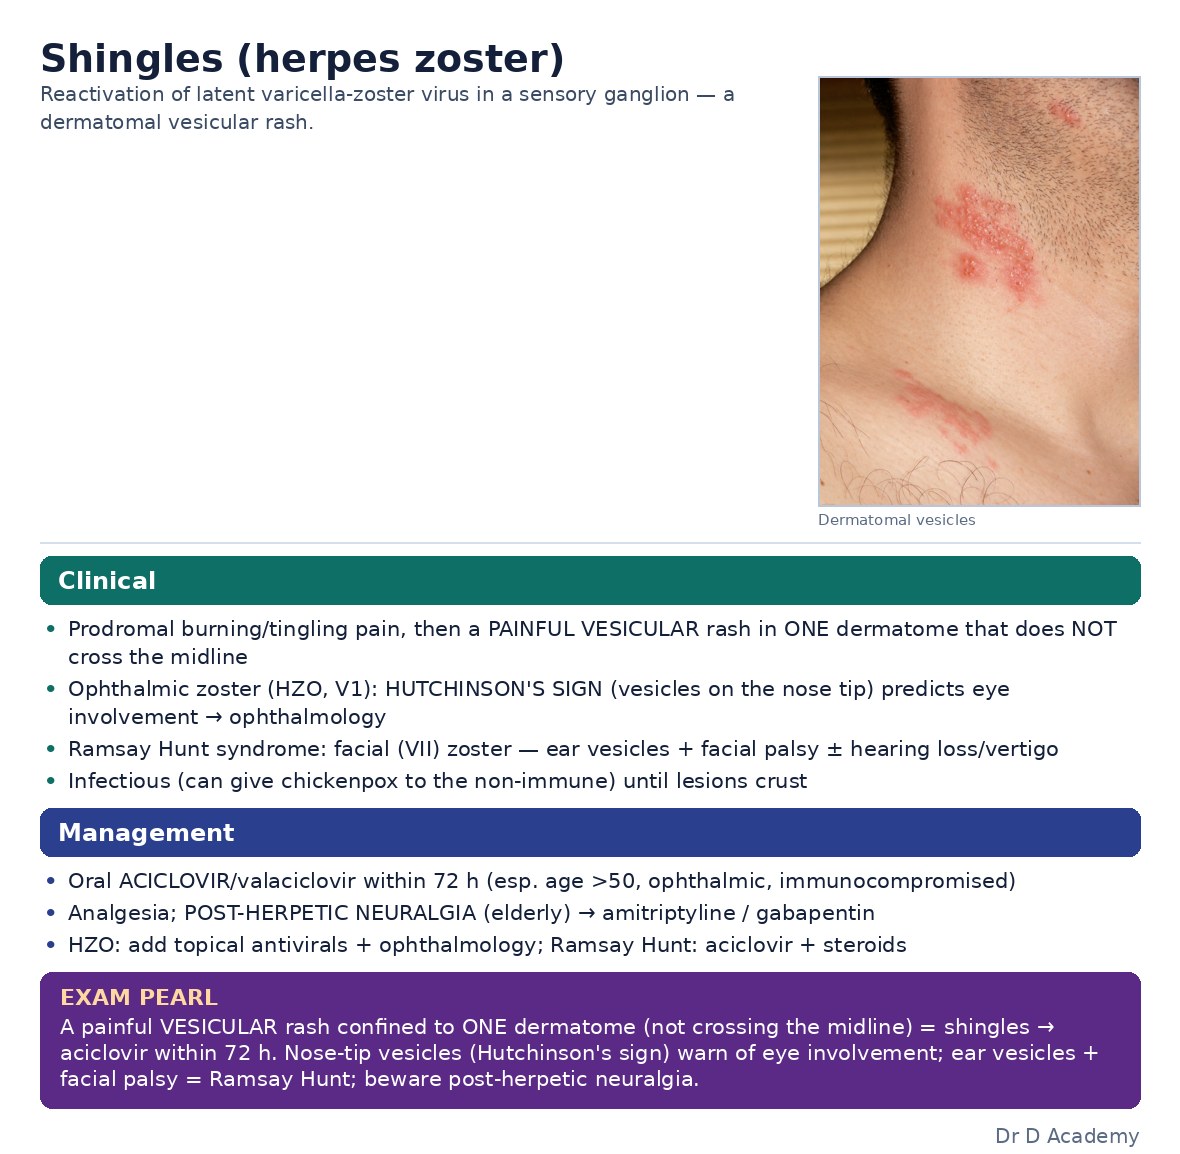
Reactivation of latent varicella-zoster virus in a sensory ganglion, giving a painful unilateral dermatomal vesicular rash. Common in elderly/immunocompromised. ED priorities: start antivirals early (ideally <72h), identify sight-threatening ophthalmic zoster, Ramsay Hunt (facial palsy), disseminated/visceral zoster in the immunocompromised, and manage pain / prevent post-herpetic neuralgia (PHN).
Figures & algorithms
Red flags
- Eye involvement / Hutchinson sign / reduced vision - sight-threatening
- Facial palsy + ear vesicles - Ramsay Hunt
- Disseminated rash or visceral symptoms in immunocompromised
- Encephalitis, myelitis, stroke (VZV vasculopathy), meningitis
- Zoster in young/recurrent - underlying immunosuppression/HIV
Assessment
Differential diagnosis
- HSV (zosteriform)
- Contact dermatitis / cellulitis / impetigo
- Early pre-eruptive zoster mimicking cardiac/renal/biliary pain
- Bullous disease
- Disseminated zoster vs primary varicella (immunocompromised)
Investigations
- Clinical diagnosis; dermatomal distribution respecting midline
- Viral PCR (vesicle swab) if atypical, immunocompromised or disseminated
- Fluorescein + slit-lamp exam if any ophthalmic involvement (Hutchinson sign = nasociliary tip lesions)
- Consider HIV test / immune workup in young patient, multidermatomal or recurrent zoster
- If disseminated: bloods, consider visceral involvement (hepatitis, pneumonitis, encephalitis)
Management
- Start oral antiviral as early as possible, ideally within 72h of rash onset; still give after 72h if new vesicles forming, ophthalmic/Ramsay Hunt, immunocompromised, or severe
- Ophthalmic zoster (V1, Hutchinson sign, red/painful eye, reduced vision): same-day ophthalmology referral + oral antivirals
- Ramsay Hunt syndrome (ear vesicles + facial palsy +/- vertigo/hearing loss): antivirals + corticosteroid + urgent ENT
- Immunocompromised, disseminated (>2 non-contiguous dermatomes / >20 lesions outside dermatome), or visceral involvement: admit for IV aciclovir and isolation
- Pain control with WHO ladder + neuropathic agents early; cover lesions, keep clean, advise contagious to non-immune (chickenpox) until crusted
- Review vaccination status - recombinant zoster vaccine (Shingrix) once recovered in eligible adults
Drugs & doses
Aciclovir 800 mg PO 5 times daily 7 days (cheapest; India first-line)
Valaciclovir 1 g PO TDS 7 days (better absorption/compliance; BNF)
Famciclovir 500 mg PO TDS 7 days (alternative) [verify local dose]
IV aciclovir 10 mg/kg (ideal body weight) IV TDS for severe/disseminated/immunocompromised/encephalitis (adjust for renal function, ensure hydration)
Reduce antiviral dose in renal impairment (CrCl <50) - check BNF
PHN / acute neuropathic pain: amitriptyline 10-25 mg nocte titrate; OR gabapentin 300 mg titrate to 300-1200 mg TDS; OR pregabalin 75 mg BD titrate (max 300 mg BD) [verify local dose]
Topical capsaicin 8% patch or 5% lidocaine plaster for localised PHN
Paracetamol + opioid (e.g. codeine/tramadol) for breakthrough acute pain
Prednisolone 60 mg OD tapering added to antiviral in Ramsay Hunt / selected severe cases [verify local]
Disposition
Most discharged with antivirals, analgesia and GP follow-up. Same-day ophthalmology for ocular zoster; ENT for Ramsay Hunt. Admit for disseminated/visceral zoster, immunocompromise needing IV therapy, CNS involvement, or intractable pain.
Complications & pitfalls
- Post-herpetic neuralgia (commonest; risk rises with age)
- Zoster ophthalmicus -> keratitis, uveitis, acute retinal necrosis, vision loss
- Ramsay Hunt -> permanent facial palsy / hearing loss
- VZV encephalitis, myelitis, large-vessel vasculopathy/stroke
- Secondary bacterial skin infection
- Disseminated/visceral zoster in immunocompromised (pneumonitis, hepatitis)
Exam pearls
- Antivirals reduce acute pain and speed healing but do NOT reliably prevent PHN (Cochrane) - start neuropathic analgesia early
- Hutchinson sign (nose-tip vesicles) predicts ocular involvement - examine the eye and refer
- Lesions are infectious to non-immune contacts (causes chickenpox) until crusted - cover and advise
- Valaciclovir/famciclovir have simpler dosing and slightly faster pain relief than aciclovir
- Recurrent or multidermatomal zoster in a young adult mandates an HIV test
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.