Mallet finger
Extensor tendon avulsion · Musculoskeletal
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
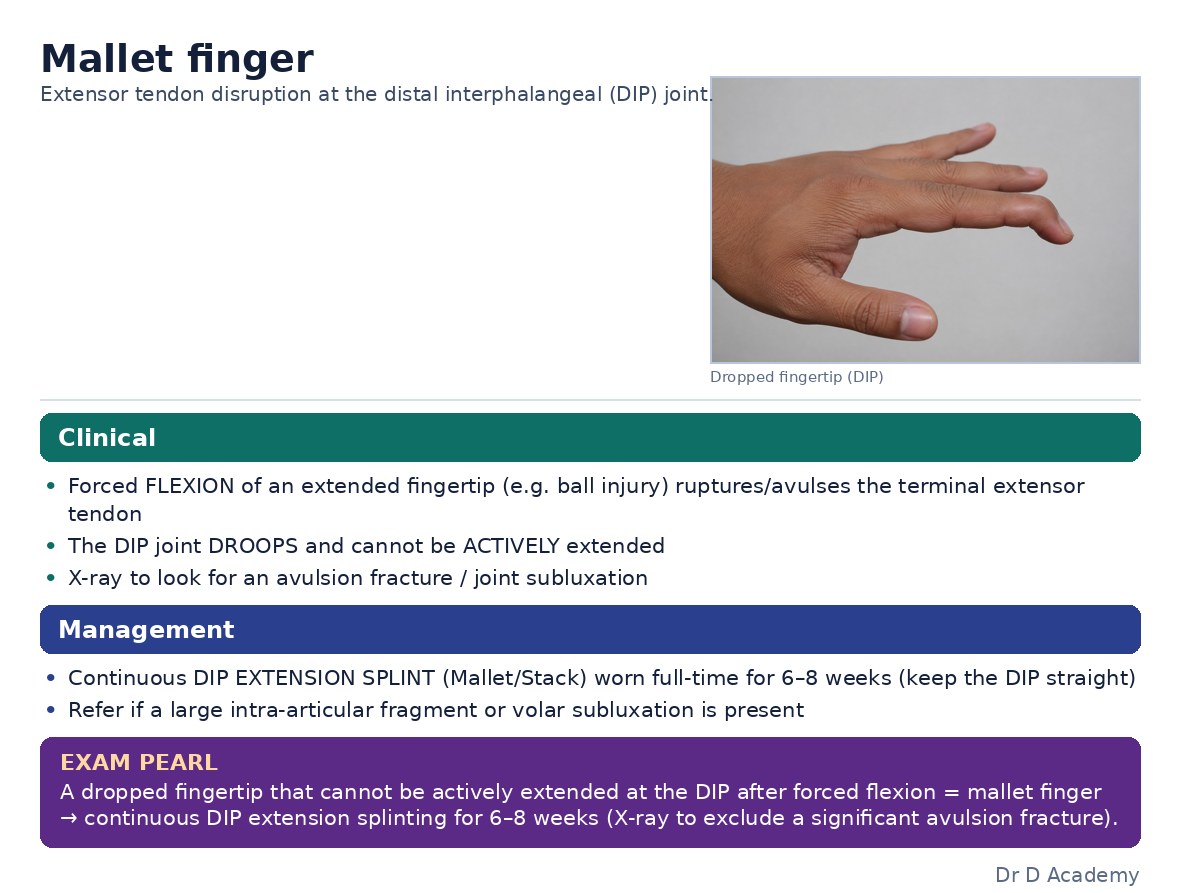
Forced flexion of an extended fingertip avulses the terminal extensor tendon (with or without a bony fragment), leaving a drooped DIP joint that cannot actively straighten. Most are treated with continuous DIP extension splinting.
Figures & algorithms
Assessment
Investigations
- Examine active DIP extension
- X-ray (bony mallet / fracture fragment, joint subluxation)
- Assess skin integrity
Management
- Splint the DIP in full extension continuously (6-8 weeks)
- Keep the DIP extended at all times during splint changes
- Analgesia
- Refer large intra-articular fragments or volar subluxation to hand surgery
- Hand clinic follow-up
Drugs & doses
Analgesia
Mallet/Stack splint
Disposition
Hand clinic follow-up.
The DIP must stay extended the whole time - letting it droop even briefly during splint changes restarts the clock.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.