Trigeminal neuralgia crisis
Severe facial pain · Neurology
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
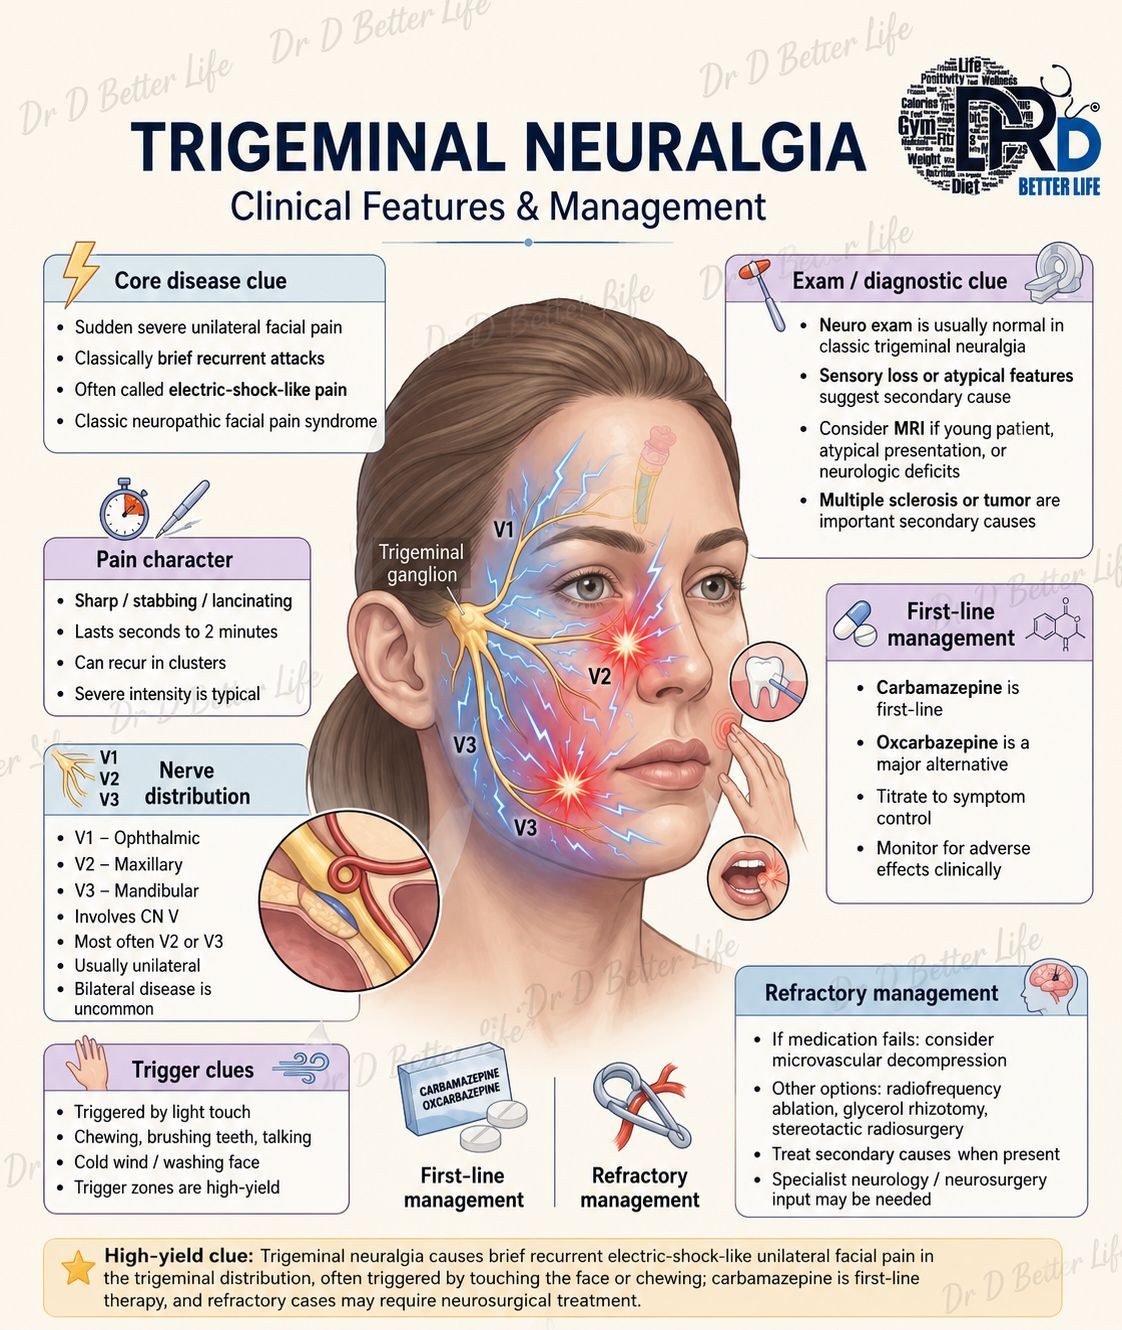
Paroxysms of severe, electric-shock facial pain in the trigeminal distribution can become so frequent that the patient cannot eat or drink, risking dehydration. Pain control (carbamazepine first-line) and excluding secondary causes are key.
Figures & algorithms
Assessment
Investigations
- Characterise the paroxysmal triggered facial pain
- Assess hydration/nutrition (may be unable to eat/drink)
- MRI to exclude a secondary cause if atypical/young/bilateral
Management
- Carbamazepine (or oxcarbazepine) first-line; titrate
- IV fluids if dehydrated; analgesia
- Consider IV/parenteral options (e.g. fosphenytoin/lidocaine) for crisis under specialist care
- Exclude secondary causes (MS, mass) with MRI
- Neurology/pain referral; surgical options for refractory cases
Drugs & doses
Carbamazepine
IV fluids
Analgesia
Disposition
Neurology; admit if dehydrated.
Trigeminal neuralgia can stop a patient eating and drinking - rehydrate, start carbamazepine, and image atypical or young patients for a secondary cause.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.