Haemolytic uraemic syndrome (HUS)
Bedside summary
A thrombotic microangiopathy defined by the triad of microangiopathic haemolytic anaemia, thrombocytopenia and acute kidney injury. Typical (STEC-HUS) follows Shiga-toxin E. coli O157 / Shigella — usually a child after bloody diarrhoea. Atypical HUS (aHUS) is complement-mediated. Renal injury predominates (vs neurological in TTP).
Figures & algorithms
Red flags
- Anuria / severe AKI, hyperkalaemia
- Fluid overload / pulmonary oedema
- Neurological features (suggests TTP or severe disease)
- Severe hypertension
Assessment
Differential diagnosis
- TTP (neuro-predominant, ADAMTS13 <10%)
- DIC (abnormal coagulation)
- Sepsis
- Malignant hypertension
- HELLP / pregnancy TMA
- Scleroderma renal crisis
Investigations
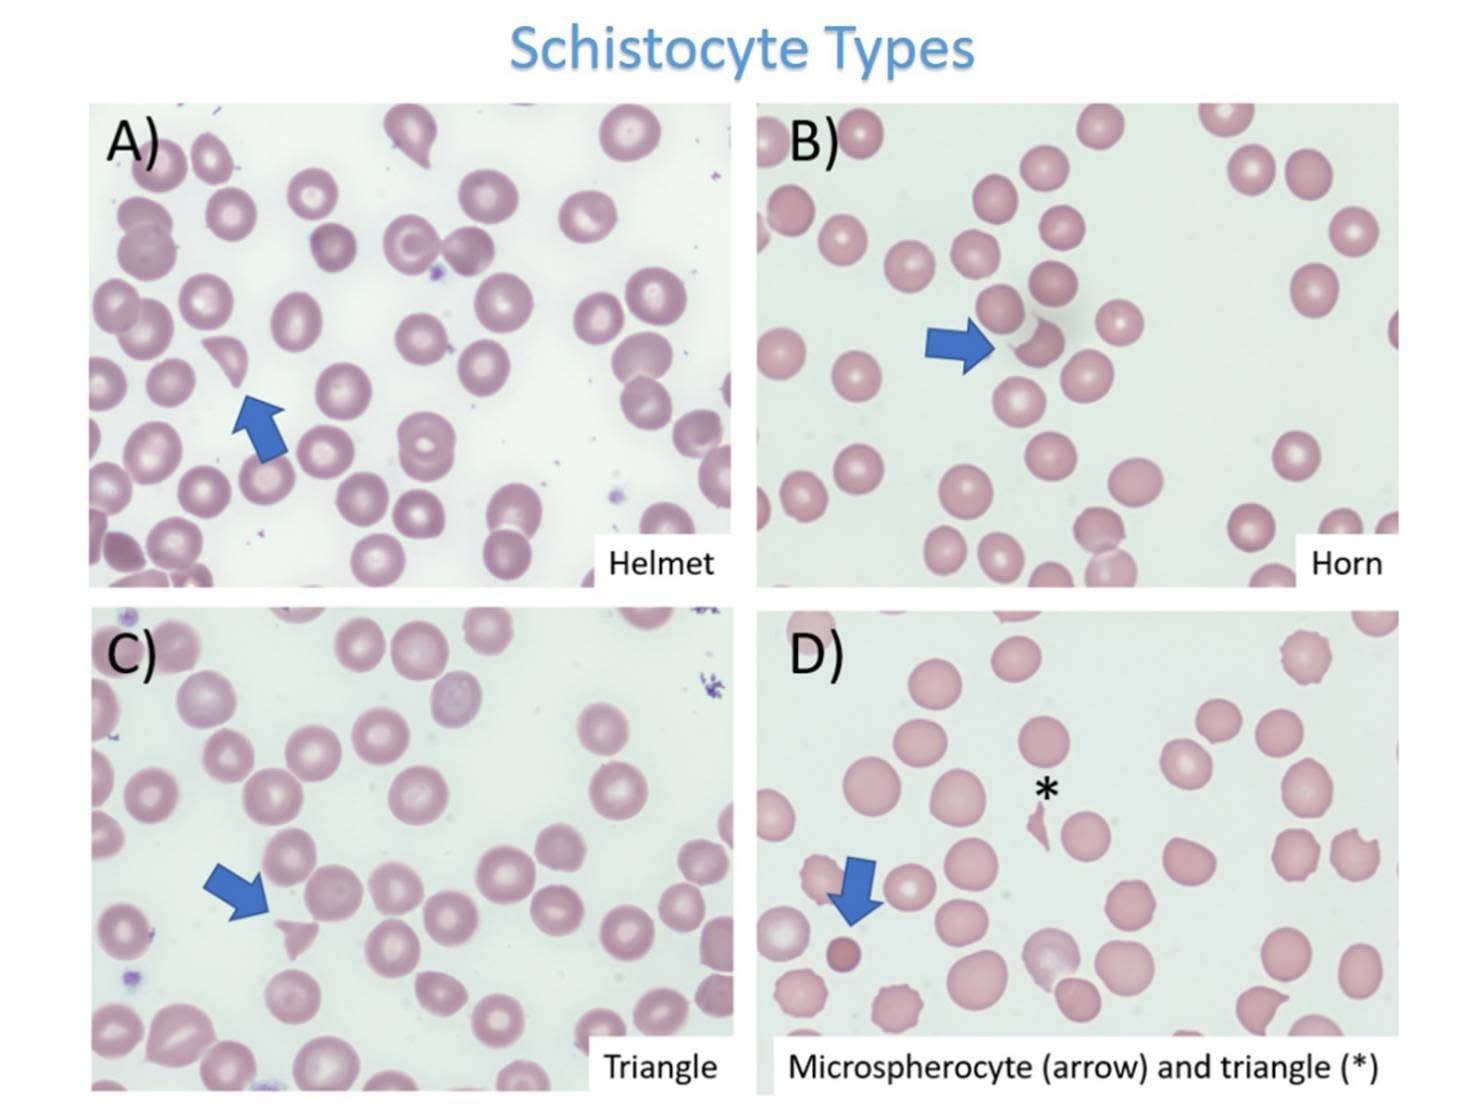
- FBC + film — schistocytes + thrombocytopenia
- U&E / creatinine — acute kidney injury
- LDH up, haptoglobin down, bilirubin up, reticulocytes up; DAT negative
- Coagulation NORMAL
- Stool culture + Shiga-toxin PCR (STEC)
- ADAMTS13 (to exclude TTP); complement studies if atypical
- Urinalysis; group & save
Management
- STEC-HUS is mainly SUPPORTIVE — careful fluid & electrolyte management, treat AKI (dialysis if needed)
- Transfuse red cells for symptomatic anaemia
- AVOID antibiotics and antimotility agents in suspected STEC (may worsen HUS)
- AVOID platelet transfusion unless life-threatening bleeding
- If TTP not yet excluded or neuro features — start plasma exchange
- Atypical HUS (no diarrhoea / recurrent) — urgent complement inhibitor (eculizumab) after meningococcal cover
- Nephrology + critical care
Drugs & doses
Disposition
Complications & pitfalls
- AKI requiring dialysis; chronic kidney disease
- Hypertension
- Neurological involvement
- Death
Exam pearls
- Child with bloody diarrhoea then falling platelets + AKI = STEC-HUS
- Do NOT give antibiotics or loperamide in suspected STEC
- Renal failure predominates in HUS; neurology in TTP
- No diarrhoeal prodrome or recurrent disease = think atypical HUS (eculizumab)
STEC-HUS is largely supportive (dialysis as needed); atypical HUS needs urgent complement inhibition. If neuro features or TTP not excluded, start plasma exchange. Antibiotic doses per BNF (current edition); confirm choice in the in-app Antibiotic Dosing tool.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.