Clostridial myonecrosis (gas gangrene)
Bedside summary
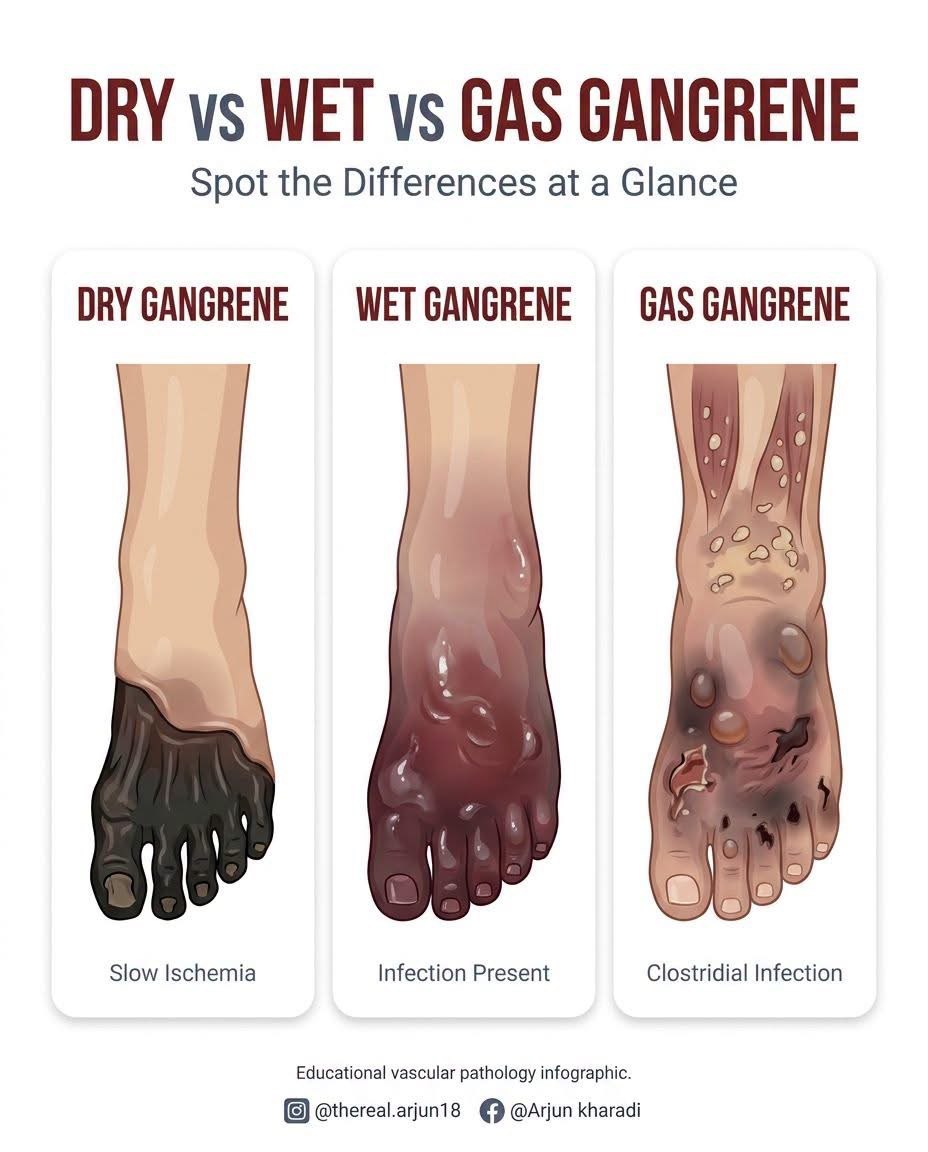
Clostridial myonecrosis is a fulminant, life-threatening necrotising infection of muscle, classically caused by Clostridium perfringens (and other clostridia) via potent exotoxins (notably alpha-toxin). TRAUMATIC gas gangrene follows a contaminated deep/crush wound or surgery; SPONTANEOUS (non-traumatic) gas gangrene is caused by C. septicum and is strongly associated with occult COLONIC MALIGNANCY or neutropenia. The hallmark is PAIN OUT OF PROPORTION to the visible findings, evolving rapidly to tense oedema, a dusky/bronze discolouration, haemorrhagic bullae, a thin “dishwater”/foul serosanguinous discharge, and CREPITUS (gas in tissues). Systemic toxaemia — tachycardia out of proportion to fever, then shock, haemolysis and multi-organ failure — advances over hours.
Figures & algorithms
Red flags
- PAIN OUT OF PROPORTION to examination findings
- Crepitus / gas in the tissues; rapidly spreading dusky, bronze skin or haemorrhagic bullae
- Systemic toxaemia — tachycardia out of proportion to fever, hypotension, confusion
- Spontaneous myonecrosis (no wound) — suspect C. septicum and occult colonic cancer/neutropenia
Assessment
Differential diagnosis
- Necrotising fasciitis (other organisms — Group A strep, polymicrobial)
- Severe cellulitis / simple abscess
- Non-infective gas in tissues (recent surgery/instrumentation)
- Pyomyositis
- Compartment syndrome
Investigations
- This is a CLINICAL, surgical diagnosis — do NOT delay theatre for tests
- Bloods: FBC (haemolysis/anaemia), U&E, CRP, lactate, CK (markedly raised), coagulation, blood cultures, group & save; Gram stain of tissue/fluid (Gram-positive rods, few neutrophils)
- Imaging (X-ray/CT) may show GAS tracking along muscle/fascial planes — but never delay surgery for imaging in an unstable patient
- Use a risk score (e.g. LRINEC) only as an adjunct — a low score does NOT exclude it
Management
- Recognise early and resuscitate aggressively (A–E, large-bore access, fluids, correct coagulopathy) while calling SURGERY and CRITICAL CARE immediately.
- Emergency SURGICAL EXPLORATION and radical DEBRIDEMENT of all necrotic tissue is the definitive, life-saving treatment — often needing repeated look-backs and sometimes AMPUTATION; do not wait for imaging or antibiotics to work.
- Start broad-spectrum IV ANTIBIOTICS urgently WITH high-dose penicillin PLUS CLINDAMYCIN (clindamycin suppresses toxin production) — e.g. a carbapenem/piperacillin-tazobactam + clindamycin ± vancomycin pending cultures.
- Supportive critical care: vasopressors, analgesia, tetanus prophylaxis, treat haemolysis/DIC and organ failure; consider hyperbaric oxygen only if it does NOT delay surgery and is locally available.
- For SPONTANEOUS (C. septicum) gas gangrene, investigate for an underlying COLONIC malignancy or immunocompromise once stabilised.
Drugs & doses
Disposition
Complications & pitfalls
- Septic shock, DIC, intravascular haemolysis and multi-organ failure
- Limb loss (amputation); extensive tissue loss
- Death — high mortality, rising with any delay to surgery
Exam pearls
- Pain out of proportion + crepitus + rapid systemic toxaemia = necrotising infection until proven otherwise — this is a SURGICAL emergency, not an antibiotics-alone problem.
- Surgery saves lives; antibiotics (penicillin + clindamycin) and critical care are adjuncts — never delay debridement for imaging or a risk score.
- Add CLINDAMYCIN for its toxin-suppressing (anti-exotoxin) effect alongside high-dose penicillin.
- Spontaneous (non-traumatic) gas gangrene → C. septicum → hunt for an occult colonic malignancy or neutropenia.
Clostridial myonecrosis kills within hours: recognise pain out of proportion, crepitus and rapid toxaemia, resuscitate, and get the patient to theatre for immediate radical debridement (the definitive treatment) — do not wait for imaging. Give high-dose penicillin PLUS clindamycin with broad-spectrum cover, support in critical care, and investigate spontaneous C. septicum cases for colonic cancer.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.