Orbital cellulitis
Sight/brain threat · Ophthalmology
Physician-written · Verified by three sets of doctors · Reviewed November 2026
Bedside summary
Infection behind the orbital septum causes proptosis, painful eye movements and visual threat, with intracranial risk. Antibiotics, imaging and ENT/ophthalmology involvement are key.
Figures & algorithms
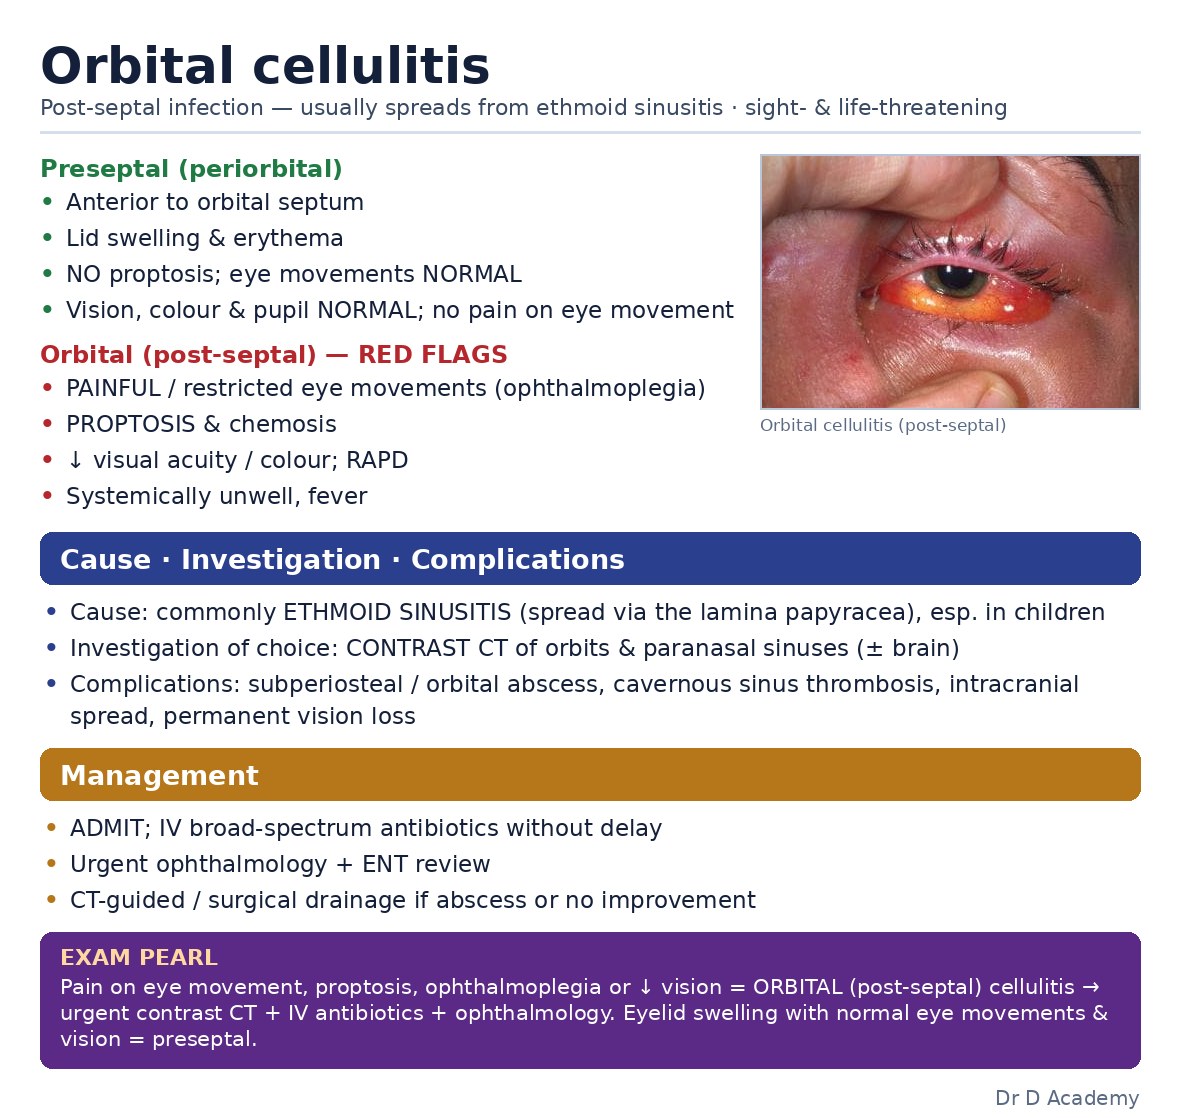
Assessment
Investigations
- Assess eye movements, proptosis and vision
- CT orbits/sinuses
- Bloods and cultures
Management
- IV antibiotics urgently
- CT to assess spread/abscess
- Ophthalmology and ENT involvement
- Monitor vision closely
- Surgical drainage if abscess
Drugs & doses
Flucloxacillin 1 g IV/PO QDS (clindamycin 600 mg QDS if penicillin-allergic) — BNF
Disposition
Admit; ophthalmology/ENT.
Painful eye movements with proptosis distinguish orbital from preseptal cellulitis. Antibiotic doses per BNF (current edition); confirm choice in the in-app Antibiotic Dosing tool.
Disclaimer: Educational decision support for qualified clinicians and students — not a substitute for clinical judgement, local protocols or a full drug reference. Confirm every dose and contraindication against your formulary before prescribing.